Subtotal $0.00

Written by George Mulaudzi, Founder & Natural Medicine Practitioner.
Erectile dysfunction (ED) is the ongoing inability to get or keep an erection firm enough for satisfying sex. It's one of the most common health concerns men face, and one of the least talked about. This guide covers everything: what ED actually is, why it happens, the different types, what the symptoms mean, and the full range of treatment options available, from lifestyle changes and natural medicine to conventional medical treatments.
Erectile dysfunction is defined as the consistent or recurrent inability to achieve or maintain an erection sufficient for sexual activity. The key words are consistent and recurrent. Almost every man occasionally fails to get an erection, after too much alcohol, under stress, when exhausted. That's normal, not ED.
It becomes ED when the problem persists over weeks or months, occurs in most sexual situations, and starts affecting your confidence or relationship. Some men can't get an erection at all; others get one but lose it too soon; others get erections that aren't firm enough for penetration. All of these fall under ED.
What Is ED?Far more common than the silence around it suggests. International research indicates that roughly half of men between 40 and 70 experience some degree of erectile difficulty (the Massachusetts Male Aging Study put the combined figure at 52%), and it's increasingly seen in younger men too, often linked to stress, lifestyle, and psychological factors rather than physical disease.
In South Africa, rising rates of diabetes and hypertension, two of the biggest physical drivers of ED, mean many men are affected earlier than they expect. If you're dealing with this, you are firmly in the majority of men at some point in their lives, not the exception.
An erection looks simple but is actually a coordinated event involving four systems:
Why this matters: ED happens when any link in that chain fails. Poor circulation, nerve damage, hormonal imbalance, or a brain preoccupied with anxiety can each break the chain, and each points to a different cause and a different treatment. This is why "one-size-fits-all" ED fixes so often disappoint.
How Erections Work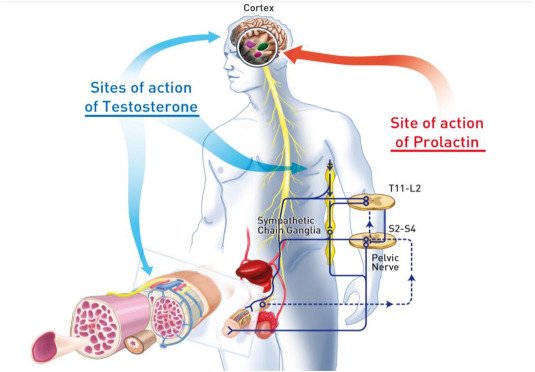
Understanding which type you have is the single most useful step toward effective treatment.
The most common physical type. Blood flow into the penis is reduced (narrowed arteries) or blood leaks out too quickly (venous leak). Strongly linked with heart disease, high blood pressure, high cholesterol, diabetes, and smoking.
Nerve signals are disrupted. Causes include diabetes-related nerve damage, spinal injuries, pelvic surgery, and neurological conditions.
Low testosterone or thyroid imbalances reduce desire and erection quality. Often accompanied by fatigue, low mood, and reduced morning erections.
The machinery works, but the mind interferes. Performance anxiety, stress, depression, relationship conflict, and guilt are common drivers.
A side effect of certain medications, including some blood pressure drugs and antidepressants, as well as recreational substances and heavy alcohol use.
In reality, most ED involves more than one factor. A physical cause creates a failure; anxiety about the failure then compounds it. This physical-psychological loop is extremely common, and treatable once recognised.
Causes fall into three broad groups, and most men have contributors from more than one.
Physical causes: diabetes, high blood pressure, heart and blood vessel disease, obesity, low testosterone, high cholesterol, prostate problems and prostate surgery, sleep apnoea, chronic kidney disease.
Psychological causes: performance anxiety, work and financial stress, depression, unresolved relationship tension, past sexual trauma, and increasingly discussed, patterns of pornography use that alter arousal responses.
Lifestyle causes: smoking (a direct blood-vessel toxin), heavy alcohol use, physical inactivity, poor diet, chronic poor sleep, and recreational drug use.
The encouraging flip side: because so many causes relate to circulation and lifestyle, ED often improves when overall health improves. Treating ED properly is frequently the same project as becoming a healthier man.
Causes of EDED tells a different story depending on when it arrives.
Signs that point toward ED rather than a passing episode:
One useful self-check: if morning and solo erections are normal but partnered sex is the problem, the cause is more likely psychological. If erections are weak or absent in all situations, a physical cause is more likely. Either way, both deserve attention, and both respond to treatment.
ED symptoms & self-assessmentThe arteries in the penis are narrower than those around the heart. When circulation starts to deteriorate, erections are often affected years before heart symptoms appear. This is why doctors sometimes call ED "the canary in the coal mine" for cardiovascular disease.
If you're experiencing persistent ED, especially if you're over 40, smoke, carry extra weight, or have a family history of heart disease or diabetes, treat it as a prompt to have your blood pressure, blood sugar, and cholesterol checked by a medical doctor. That check-up could matter far beyond your sex life.
We say this as a natural medicine practice without hesitation: natural treatment and conventional medical screening are not rivals. Every man with persistent ED should know his cardiovascular numbers.
There is no single "best" ED treatment, there's the right treatment for your causes. The main categories:
Lifestyle change: the foundation under every other treatment. Stopping smoking, reducing alcohol, exercising, improving diet and sleep. For milder vascular and lifestyle-driven ED, this alone can restore function over time.
Natural and naturopathic treatment: our specialisation. Protocols targeting circulation, hormonal balance, nutrition, stress, and overall vitality, aimed at addressing root causes for durable, long-term improvement rather than one-night fixes.
Conventional medical treatments: oral medications (PDE5 inhibitors such as sildenafil and tadalafil), injections, vacuum devices, hormone therapy where clinically indicated, and surgical implants in severe cases. These are legitimate, effective options for many men, typically accessed through a medical doctor or urologist. They generally treat the symptom rather than the cause, which is why many men combine them with, or eventually replace them through, root-cause approaches.
Psychological support: counselling or sex therapy where anxiety, depression, or relationship factors are driving the problem. Often the missing piece in "mixed" ED.
 5.05.0Top Rated ServiceVerified by TrustindexTop Rated Service
- 5.0 Excellent rating Last 12 months
- New reviews collected regularly Recent review activity detected
- Responds to customer reviews 100% response rate within 48 hours
- Verified by Trustindex Based on real customer reviews Learn more
Posted on Google
 Sbongakonke Myeni37 days ago
Trustindex verifies that the original source of the review is Google.
Good service and friendly staff.Posted on Google Philani Philastzozi39 days agoGood service and professional customer are. Philani from SoshanguvePosted on Google
 Mahlangu Mdu48 days agoExcellence service and professional staff. I am very hapy with the results. Thank you for taking care of my problem, Mr Mahlangu from Pretoria East
Five questions, answered only in your browser. Nothing is sent anywhere, nothing is stored and nobody at the clinic sees your answers. It is an educational prompt to help you decide whether to get assessed, not a diagnosis.
1. Over the past three months, how often could you get an erection firm enough for sex?
2. When you did get an erection, how often did it last long enough to finish sex?
3. In the past month, have you noticed morning or spontaneous erections?
4. Do you live with diabetes, raised blood pressure, raised cholesterol or a heart condition?
5. How much is this affecting your mood, your confidence or your relationship?
Seek urgent medical care if you have an erection lasting more than four hours, if erections stop suddenly alongside numbness, weakness or slurred speech, or if you get chest pain or breathlessness during exertion or sex.
Most men expect an examination. The first appointment is mainly a conversation, and that conversation does more diagnostic work than any test.
The opening questions matter most: when the difficulty started, whether it arrived gradually or suddenly, whether you still wake with erections, and what else changed around the same time. A new medicine. A harder year at work. Weight gained. Sleep lost.
That pattern points somewhere. Difficulty that appeared suddenly in a man who still wakes with erections points in a very different direction from difficulty that has crept in over two years alongside rising blood pressure.
The first round of tests is simple, and any GP or clinic in South Africa can do it: blood pressure, blood glucose or HbA1c, a cholesterol panel, and often a morning testosterone measurement. Waist circumference is worth measuring too. None of it needs a specialist, and it is where an assessment should begin wherever you live.
More specialised investigation, such as a fuller hormonal work-up, penile Doppler ultrasound or overnight tumescence testing, belongs with a urologist and is not needed in most cases.
Our guide to erectile dysfunction assessment and testing covers each test and what the results mean. It is also worth checking whether a medicine you already take could be contributing.
Where to actually go, in both the public and private systems.
Start with a GP or a clinic. In the public system that means your nearest clinic or community health centre, which refers on to a district hospital and, where needed, to a tertiary hospital. In the private system it means a GP, who can refer to a urologist. Either way the GP stage is not a formality to skip. Blood pressure, glucose, cholesterol and a medication review are the first real steps, and a GP can do all four.
Tertiary urology is concentrated. Groote Schuur and Tygerberg in the Western Cape, Inkosi Albert Luthuli in KwaZulu-Natal, Universitas in the Free State, the Polokwane and Mankweng complex in Limpopo, Livingstone in the Eastern Cape, Robert Mangaliso Sobukwe in the Northern Cape, and several academic hospitals in Gauteng. Access is by referral, not by presenting directly, and in some provinces the nearest specialist is a long drive.
Say what it is. Erectile difficulty is a legitimate reason to ask for a cardiovascular screen, and it is worth saying so plainly rather than hoping it comes up. In men over about forty it can be the first noticeable sign of a vascular problem, which is a good reason to raise it early rather than wait.
Consultation costs vary widely between the public and private routes. Ours are set out on the consultation cost page, and the South African statistics page gives a sense of how common this is locally.
Sometimes. It depends entirely on the cause, which is why identifying the cause matters more than picking a treatment.
Difficulty driven by a medicine often resolves once the prescriber adjusts it. Difficulty driven by alcohol, poor sleep, being badly deconditioned or a period of acute stress frequently improves when those change. Difficulty driven by early vascular or metabolic disease often improves substantially when the underlying condition is treated properly.
Difficulty caused by established nerve damage, significant arterial disease or surgical injury is usually managed rather than reversed. Managed well, with options that work, but managed.
What nobody can honestly promise is a permanent cure, and anyone who does is worth being wary of. More detail in is erectile dysfunction permanent and in our comparison of treatment options.
Largely the same things that protect your heart, which is not a coincidence.
The arteries that supply the penis are narrow, and they tend to be affected before the larger ones. That is why erectile function works as a reasonably sensitive early indicator of vascular health, and why what protects one protects the other.
Not smoking. Blood pressure, glucose and cholesterol kept in range. Regular aerobic exercise. Weight around the middle. Alcohol within sensible limits. And sleep, which is the most underrated item on this list by some distance.
None of that is novel advice, and that is rather the point. See exercise and erectile function, diet, and smoking and alcohol.
The part most clinical pages leave out.
There is a pattern that shows up repeatedly. One difficult occasion leads to worry about the next. Worry makes the next one more likely to go the same way. Sex starts being avoided, and the avoidance is easier to manage than the conversation. Within a few months the problem is no longer only physical.
Partners frequently read it as loss of attraction. That is the single most common misreading, and it is usually wrong. In the absence of any explanation, it is also the most available one. Saying nothing tends to do more damage than an awkward conversation would have.
Relationship strain is a legitimate reason to seek help, even when the underlying cause turns out to be entirely physical. Our guide on talking to your partner about erectile dysfunction covers how to open it, and psychological causes covers the anxiety loop in more depth.
A short list, separate from the general warning signs, because these do not wait.
An erection lasting more than four hours. This is priapism and it is a same-day emergency. Prolonged erections can cause permanent tissue damage, and the window for treating it is measured in hours.
Chest pain, breathlessness on exertion, or pain spreading to the jaw or arm. Go to an emergency department. This is not an erectile dysfunction problem.
Sudden and complete loss of erectile function after an injury, an operation or starting a new medicine needs urgent medical assessment rather than a naturopathic consultation.
Numbness in the groin or inner thighs, or new problems controlling your bladder or bowel. Urgent. These can indicate nerve compression.
Short appointments go better when you arrive knowing what to ask.
Could any of the medicines I take be causing or worsening this? Should my blood pressure, blood glucose and cholesterol be checked? Does this look more like circulation, hormones, medication, or something psychological? Do I need a specialist, or can this be handled here? What would you try first, and how long before we know whether it is working?
Our consultation checklist is a printable version of this.
This guide draws on recognised clinical guidance and peer-reviewed research on erectile dysfunction, cardiovascular risk and metabolic health.
Written and reviewed by George Mulaudzi, Naturopath, Erectile Dysfunction Clinic. This guide provides general educational information and is not a substitute for personalised medical advice, diagnosis or emergency care. Erectile dysfunction can be associated with cardiovascular, hormonal, neurological, medication-related or psychological factors. Do not stop or change prescribed treatment without speaking to the prescribing healthcare professional. Seek medical assessment when symptoms are sudden, severe, persistent or accompanied by other concerning symptoms.
Naturopathic care complements necessary medical care. It does not replace it. Where a GP, urologist, cardiologist or emergency department is the right route, you will be told so directly. Our editorial and medical review policy sets out how this content is produced and checked.
Is ED permanent? Usually not. Most ED has identifiable, addressable causes. Even where an underlying condition can't be cured, erectile function can very often be significantly improved.
Can ED go away on its own? Sometimes, particularly stress-related episodes. But persistent ED (weeks to months) rarely resolves without addressing its cause, and waiting can allow anxiety to entrench the problem.
Does ED mean low testosterone? Not necessarily. Low testosterone is one possible cause among many. Circulation and psychological factors are more common culprits.
Is ED only an older man's problem? No. It's more common with age, but young men experience it too, usually with different causes and equally good prospects for improvement.
Should I see someone about occasional failure? Occasional failure is normal. See someone when the problem is persistent, worsening, or affecting your confidence or relationship.
You've just learned more about ED than most men ever do. If you'd like to understand your own situation, what type, what causes, what to do about it, book a confidential consultation at our Sandton practice.